


You rolled your ankle a while back. The swelling went down, the bruising cleared, and you thought you were fine. But weeks or months later, the ankle still wobbles on uneven ground. It catches you off guard when stepping off a curb. It gives out on a run, on a hiking trail, or sometimes even while walking across a parking lot. You have started second-guessing every step on uneven terrain. That pattern has a name: chronic ankle instability(CAI). And it is far more common than most people realize.
What Is Chronic Ankle Instability
Chronic ankle instability (CAI) is not just a weak ankle or bad luck. It is a well-defined condition; a structural and neurological aftermath of an incompletely healed lateral ankle sprain,: and it is far more common than most people realize.
Technically, chronic ankle instability refers to repetitive bouts of lateral ankle instability resulting in numerous ankle sprains, with a feeling of giving way and apprehension in the ankle persisting for a minimum of six months after the original injury.
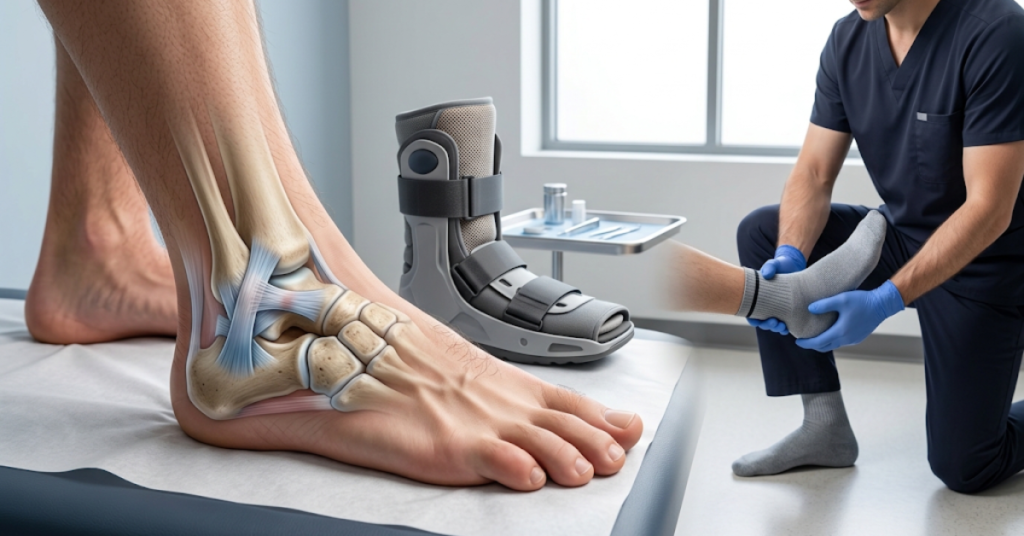
The ankle joint is stabilized by a group of lateral ligaments, primarily the anterior talofibular ligament (ATFL) and the calcaneofibular ligament (CFL). When these are stretched or torn during a sprain and do not heal with full structural and neurological integrity, two separate but related problems develop.
Mechanical instability means the ligament tissue itself has healed in a lengthened or lax state, reducing the physical restraint that prevents the joint from rolling.
Functional instability means the proprioceptive nerve receptors embedded in the ligament tissue have been damaged, impairing the sensory feedback system that tells your brain where your ankle is in space and triggers the protective muscle responses that catch you before you fall.
Most patients with chronic ankle instability have both. That combination is why the ankle keeps giving out, even when the original sprain feels long healed.
How Common Is Chronic Ankle Instability
Ankle sprains are among the most common injuries in both athletic and everyday populations. Ankle sprains affect approximately 8% of the general population, and recurrence occurs in as many as 80% of patients participating in high-risk sports.
Of everyone who sustains a lateral ankle sprain, up to 70% develop chronic ankle instability. That figure is striking. The majority of ankle sprains, when inadequately rehabilitated, do not simply heal and resolve. They become a chronic condition that persists indefinitely without appropriate management.
Research from the Zhongnan Hospital of Wuhan University notes that approximately 60% of individuals have experienced ankle sprains, making chronic ankle instability one of the most prevalent musculoskeletal conditions in the general adult population, particularly in active individuals.
Why a Single Sprain Becomes a Chronic Problem
The transition from one ankle sprain to chronic instability is almost always driven by the same thing: inadequate initial management.
When the pain and swelling from an acute sprain subside, most patients assume the injury has healed. Clinically, that assumption is wrong. The reduction of acute inflammation does not indicate ligament healing. It indicates the end of the inflammatory phase. The ligament is still structurally compromised, the proprioceptive deficit is still present, and the neuromuscular control system has not been retrained.
If the patient returns to full activity without structured rehabilitation, the ankle is set up to roll again. And again.
Each subsequent sprain causes additional cumulative ligament damage. The proprioceptive deficit deepens with every episode. The peroneal muscles, which serve as the primary active stabilizers of the lateral ankle, become slower to react and easier to fatigue. What started as a single acute injury evolves into a persistent pattern of mechanical and functional instability.
Chronic ankle instability is associated with persistent problems at least 12 months after an initial lateral ankle sprain. Individuals often experience changes in strength, range of motion, motor control, and other factors.
The critical insight is that this progression is not inevitable. It is the predictable consequence of undertreated initial sprains, and it is largely preventable with appropriate early rehabilitation.
Recognizing the Symptoms
Chronic ankle instability presents differently from an acute sprain. The symptoms are often subtler, more intermittent, and more easily dismissed as residual weakness or general clumsiness. The most common clinical features include the following.
A persistent feeling that the ankle is unreliable or that you cannot fully trust it. Repeated episodes of the ankle giving way during walking, running, or cutting movements. Heightened anxiety about uneven terrain, stairs, or activities that require lateral movement. A history of multiple sprains to the same ankle, often with progressively less force required to cause each subsequent episode. Reduced single-leg balance compared to the other side. Chronic low-grade aching around the lateral ankle, particularly after activity.
It is worth distinguishing chronic ankle instability from a simple weak ankle. A weak ankle feels fatigued or unsupported but does not give way unexpectedly. Chronic ankle instability is specifically characterized by involuntary giving-way episodes, often with little or no warning.
What Happens to the Joint If It Goes Untreated
Chronic ankle instability carries consequences that extend well beyond repeated sprains. Every time the ankle gives way, the joint surfaces sustain impact loading at abnormal angles. Cartilage damage accumulates incrementally. The peroneal tendons sustain repeated stretch injuries that can progress to tendonitis, partial tears, or subluxation.
Acute lateral ankle instability might progress to a chronic state when the ankle fails to regain its normal functional and mechanical stability after the injury. Over time, the abnormal joint mechanics of chronic instability accelerate cartilage wear and increase the risk of early-onset ankle osteoarthritis.
Risk factors for treatment failure after surgical stabilization include generalized joint laxity, high-level sports activities, female sex, varus hindfoot alignment, poor quality of the remnant lateral ligaments, and intraoperative syndesmosis widening. Understanding these factors informs both conservative and surgical treatment planning.
The longer chronic ankle instability goes unaddressed, the more structural damage accumulates in the joint, and the more complex the eventual treatment becomes.
How Chronic Ankle Instability(CAI) Is Diagnosed
Accurate diagnosis is the foundation of effective treatment. The clinical evaluation for chronic ankle instability typically includes the following components.
History taking to document the original injury mechanism, the number and frequency of subsequent sprains, what activities trigger giving-way, and any prior treatment received.
Physical examination including the anterior drawer test, which assesses how much the talus slides forward in the ankle socket and indicates ATFL laxity, and the talar tilt test, which measures side-to-side joint tilting and reflects CFL integrity. Single-leg standing tests reveal how well the ankle’s nerve signaling is functioning.
Imaging starting with weight-bearing X-rays to assess bony alignment and identify any avulsion fractures from prior sprains. MRI or diagnostic ultrasound is used when significant ligament damage, osteochondral lesion, or peroneal tendon pathology is suspected and needs to be confirmed before finalizing the treatment plan.
Gait analysis to identify biomechanical contributors, particularly supination, varus hindfoot alignment, and abnormal landing mechanics, that increase lateral ankle ligament stress during activity.
Treatment of CAI requires a multifaceted algorithm, involving historical analysis, clinical evaluations, and diagnostic imaging. The specific type and severity of the instability, mechanical, functional, or both, directly determines the most appropriate treatment approach.
Treatment Options for Chronic Ankle Instability
The evidence robustly supports a paradigm shift from a generic prescription of exercise to a deficit-targeted personalized approach. Effective chronic ankle instability treatment begins with identifying which specific deficits are present in each patient and targeting them directly.
Proprioceptive and Neuromuscular Rehabilitation
This is the most important and most underutilized component of conservative treatment. Because functional instability involves a deficit in the sensory feedback system rather than structural laxity alone, exercises that specifically challenge and retrain ankle joint position sense are essential.
Exercise therapy is considered an effective treatment for patients with chronic ankle instability, with significant improvement in functional ankle ability scores observed across 15 randomized controlled trials involving 586 participants.
A 2026 systematic review and meta-analysis published in the Journal of Foot and Ankle Research found that combining balance and strengthening exercises provides complementary benefits addressing both proprioceptive and strength deficits simultaneously in chronic ankle instability patients. The program should be progressive, beginning with basic single-leg balance and advancing through sport-specific dynamic movements as stability improves. PubMed Central
Peroneal Strengthening
The peroneal muscles are the primary dynamic stabilizers of the lateral ankle. In patients with chronic ankle instability, they are consistently found to be both weak and slow to activate. Balance and proprioception assessment through single-leg standing tests reveals how well the ankle’s nerve signaling is functioning, which directly informs the strength and speed components of the rehabilitation program.
A targeted peroneal strengthening program improves the active protection available to the ankle even before proprioceptive retraining has fully restored the sensory feedback system.
Ankle Bracing
External ankle bracing provides mechanical support during the rehabilitation phase, allowing patients to remain active without the risk of additional ligament damage from a giving-way episode. Bracing is most valuable during the early-to-middle stages of rehabilitation and is gradually weaned as functional stability is restored. It does not replace rehabilitation but enables it.
Orthotic Management
Biomechanical contributors, particularly supination and varus hindfoot alignment, increase the mechanical stress on the lateral ankle ligaments during walking and sport. Custom orthotics correct these contributors by altering how force is distributed through the foot and ankle during activity, reducing the lateral loading pattern that drives instability. They are most effective when fabricated following a comprehensive gait analysis rather than prescribed generically.
Activity Modification
During the active rehabilitation phase, modifying activities to reduce giving-way risk while maintaining fitness is an important practical component of management. Low-impact cardiovascular activities that do not place lateral stress on the ankle, such as swimming and cycling, maintain conditioning while the proprioceptive and strength deficits are addressed.
Surgical Stabilization
Conservative management is successful for the majority of patients. Approximately 20 to 30% of patients experience persistent mechanical or functional instability requiring surgical intervention despite a complete course of conservative care.
The gold standard surgical procedure is the Broström-Gould repair, in which the stretched or damaged lateral ligaments are shortened and tightened to restore native mechanical stability. In recent years, arthroscopic techniques have grown in popularity due to their minimally invasive nature, ability to address concomitant intra-articular pathology, and favorable recovery profiles compared to open surgery.
Surgery is suggested when patients continue to have symptoms after 3 to 6 months of nonsurgical treatment and have indications of chronic lateral ankle instability on physical and imaging examinations. Post-operative rehabilitation is essential to restore proprioception and strength alongside the structural correction.
Prevention and Reducing Recurrence Risk
For patients who have experienced one or more ankle sprains, targeted prevention significantly reduces the risk of progressing to chronic instability.
Balance and proprioception training is the single most evidence-supported intervention for reducing ankle sprain recurrence. A consistent program of single-leg balance exercises, including progressively challenging surfaces and movements, retrains the neuromuscular response that catches the ankle before it rolls.
Appropriate footwear for the activity and foot type, gradual progression of training loads following the 10% rule where weekly mileage or intensity is never increased by more than 10%, and regular calf and ankle mobility work all contribute meaningfully to ankle sprain prevention.
For patients with existing chronic instability, the most important preventive measure is completing a full, structured rehabilitation program rather than returning to activity as soon as acute symptoms resolve.
When To See a Podiatrist for Ankle Instability
Many patients with chronic ankle instability delay seeking care because they assume repeated ankle rolling is simply part of their anatomy or a consequence of their chosen sport. Neither is true. Chronic ankle instability is a treatable condition, and outcomes are consistently better when treatment begins early, before the cumulative joint damage from repeated giving-way episodes has progressed.
Seek a podiatric evaluation if your ankle has given way more than twice, if you feel apprehension or anxiety about footing on uneven terrain, if you have noticed progressive weakness or reduced balance on the affected side, or if you have sustained multiple sprains to the same ankle without a clear resolution of instability between episodes.
Early evaluation allows the specific type and severity of the instability to be characterized accurately, the correct treatment approach to be selected, and the rehabilitation to begin before further structural damage accumulates.
Frequently Asked Questions About Chronic Ankle Instability(CAI)
How is chronic ankle instability different from a weak ankle?
A weak ankle produces fatigue and reduced endurance but does not give way involuntarily. Chronic ankle instability is characterized by unexpected giving-way episodes driven by a combination of mechanical ligament laxity and proprioceptive deficit. A weak ankle responds to general strengthening. Chronic ankle instability requires targeted proprioceptive retraining alongside strength work to address the neurological component of the deficit.
Can chronic ankle instability resolve without treatment?
Rarely. Because the condition involves both structural laxity and a neuromuscular deficit, neither component self-corrects with rest alone. The proprioceptive deficit in particular requires specific retraining to restore. Without structured rehabilitation, instability tends to persist and worsen with each subsequent sprain as additional cumulative ligament damage occurs.
How long does rehabilitation for chronic ankle instability take?
Most patients see meaningful improvement within six to twelve weeks of consistent structured rehabilitation. Full functional stability, particularly for athletes returning to high-demand cutting and jumping sports, typically takes three to six months. The exact timeline depends on the severity of the instability, the specific deficits present, and how consistently the rehabilitation program is followed.
Does chronic ankle instability always require surgery?
No. The majority of patients respond well to conservative management including proprioceptive rehabilitation, peroneal strengthening, bracing, and orthotic correction of biomechanical contributors. Surgery is reserved for patients who have completed a full course of conservative care without adequate resolution, or for those with significant mechanical laxity or associated intra-articular pathology that makes conservative treatment unlikely to succeed.
Does chronic ankle instability lead to arthritis?
Yes, over time. Repeated giving-way episodes subject the ankle joint cartilage to abnormal impact loading at abnormal angles, accumulating microtrauma that increases the risk of early-onset ankle osteoarthritis. This is one of the primary reasons why early treatment is preferable to a long period of untreated instability.
Getting Help for Chronic Ankle Instability in Valparaiso, IN
If your ankle keeps giving out and you are in the Valparaiso, Portage, Chesterton, or wider Northwest Indiana area, Dr. Harpreet Minhas at Sole Foot and Ankle provides comprehensive evaluation and chronic ankle instability treatment in Valparaiso, IN. The evaluation includes clinical ligament testing, gait analysis, on-site digital X-ray, and where needed, MRI referral to fully characterize the instability before treatment is planned.
📞 +1 219-464-9588
📍 2308 Roosevelt Rd, Valparaiso, IN 46383
🔗 solefootdoc.com
Sole Foot and Ankle. One Step Ahead.



